Ulixertinib (BVD-523) Ulixertinib inhibitor targeting ERK1/2 in KRAS-Driven Metastatic Pancreatic Cancer
Copy code to add this image to your page
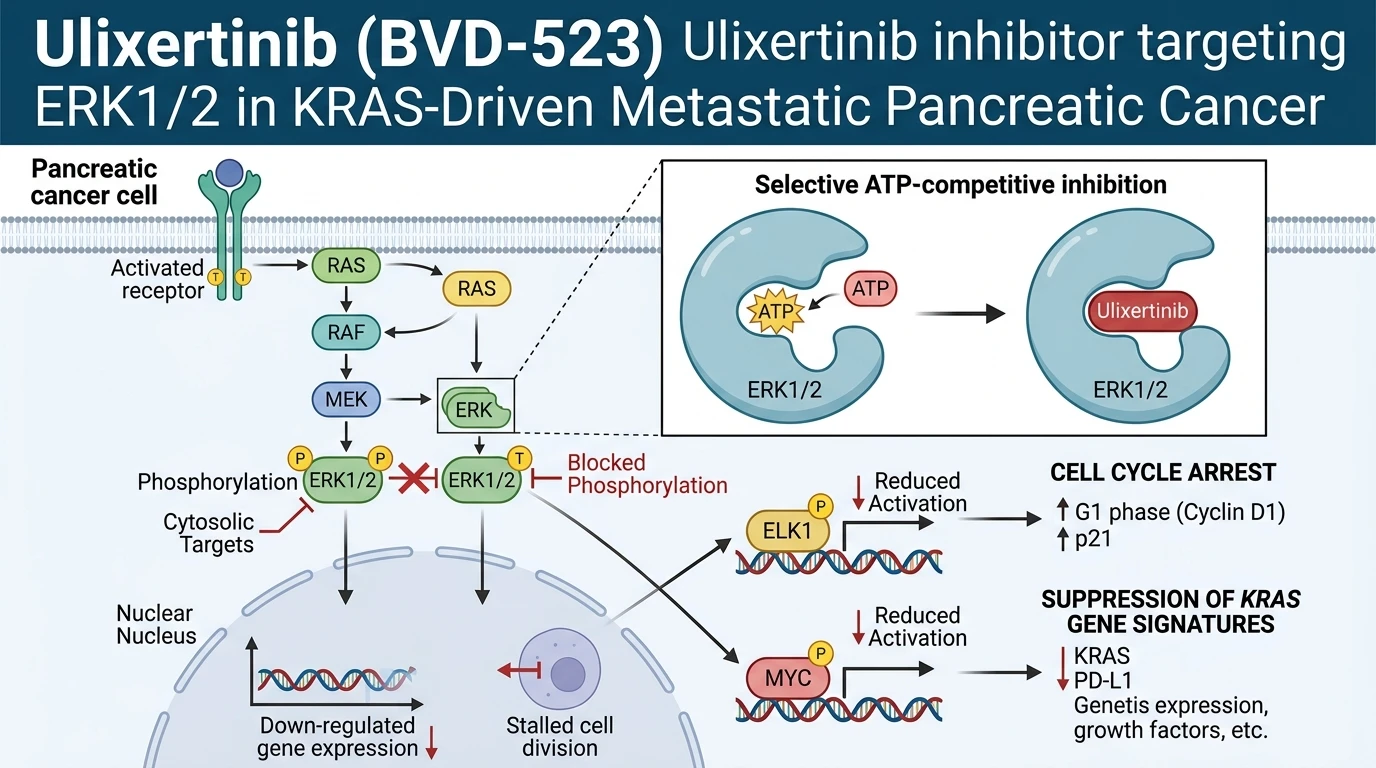
Pancreatic ductal adenocarcinoma (PDAC) remains one of the most recalcitrant malignancies in medical oncology, characterized by a high prevalence of oncogenic KRAS mutations exceeding 90% of cases. Upstream signaling nodes, such as EGFR or RAS itself, frequently trigger compensatory feedback loops when inhibited in isolation. Consequently, targeting terminal node effectors within the Mitogen-Activated Protein Kinase (MAPK) cascade presents a compelling pharmacological target. The small molecule Ulixertinib (BVD-523) was developed as a potent, highly selective, reversible ATP-competitive ERK1 and ERK2 inhibitor designed to suppress signaling downstream of MEK. By directly binding the kinase domain of ERK1/2, this agent blocks substrate phosphorylation regardless of upstream RAF or MEK mutational status or receptor tyrosine kinase reactivations.
In a phase Ib clinical investigation evaluating treatment-naive patients with metastatic PDAC, ulixertinib was combined with standard frontline chemotherapy consisting of gemcitabine and nab-paclitaxel (GnP). The primary objective involved determining safety, tolerability, maximum tolerated dose, and preliminary therapeutic efficacy. Pharmacodynamic evaluations incorporated pre- and post-treatment tumor tissue biopsies subjected to high-throughput RNA-sequencing. Transcriptomic profiling provided clear biological evidence of intratumoral target engagement. Administration of the triplet regimen resulted in a significant downregulation of established KRAS-dependent gene expression signatures, confirming that effective pharmacological concentration was achieved within the tumor microenvironment under tested clinical conditions.
Despite clear mechanistic target engagement, clinical utility was severely constrained by systemic toxicity. The addition of the PubChem compound database entries for targeted kinase and proteasomal inhibitors illustrate the delicate balance between structural specificity and physiological tolerability. In this PDAC cohort, the triplet combination induced frequent all-grade treatment-related adverse events (TRAEs). Fatigue, severe nausea, vomiting, diarrhea, generalized maculopapular rash, and profound hematologic cytopenias occurred at high frequencies. These toxicities mandated frequent protocol-specified dose reductions, prolonged treatment interruptions, and ultimately high rates of voluntary patient withdrawal, leading to early termination of the clinical trial.
Among the subset of evaluable patients who maintained therapeutic dosing prior to discontinuation, objective responses were observed. The confirmed overall response rate (ORR) reached 20%, accompanied by a median progression-free survival (PFS) of 5.46 months and a median overall survival (OS) of 12.23 months. These efficacy parameters closely parallel historically established benchmarks achieved with standard GnP doublet therapy alone. The absence of superior survival metrics highlights the challenge of incorporating continuous ERK1/2 inhibition into toxic cytotoxic backbones. Overall, the trial demonstrated that while ulixertinib successfully suppressed downstream MAPK transcriptional outputs in human PDAC tissues, continuous high-dose administration combined with multi-agent chemotherapy is limited by cumulative off-target and systemic toxicities.
Pharmacological Characterization and Clinical Feasibility Assessment
Copy code to add this image to your page
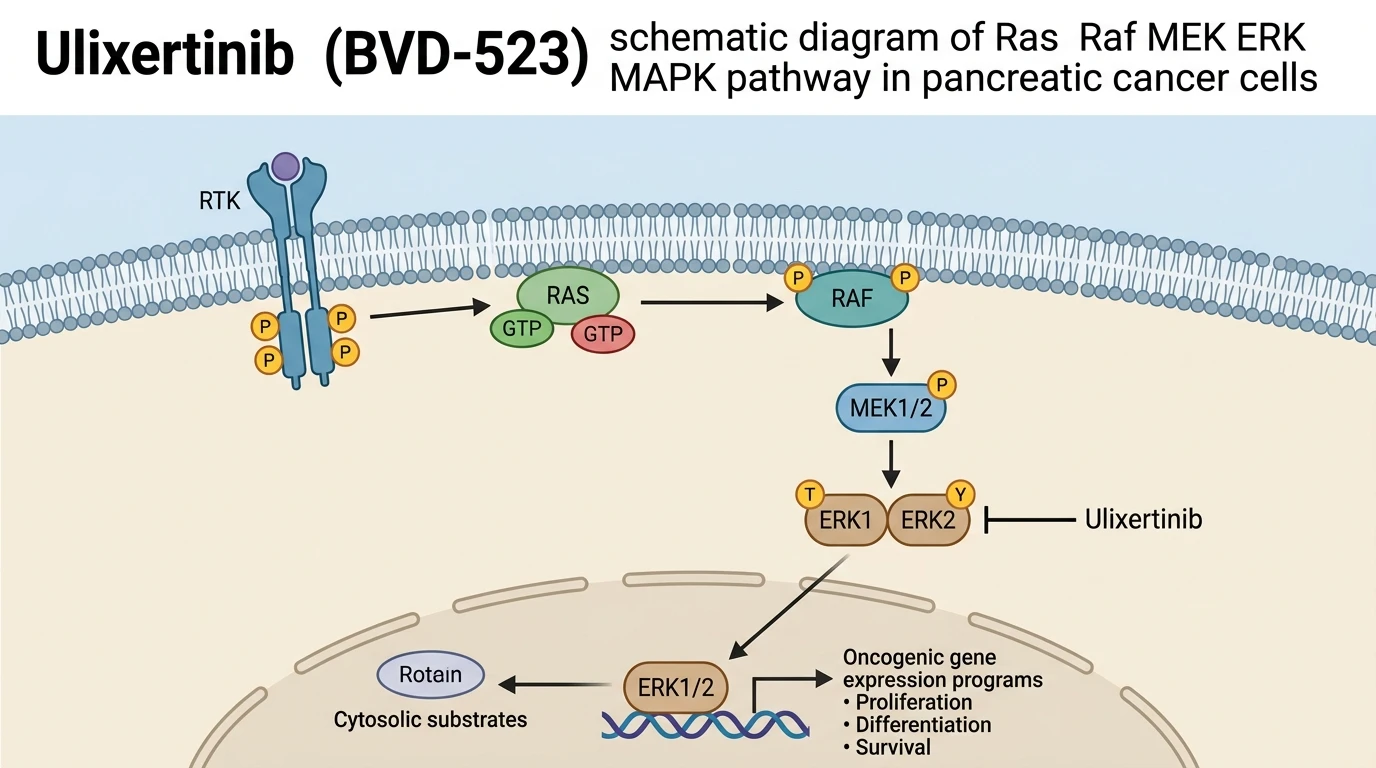
Ulixertinib (BVD-523) functions as a novel, highly selective, reversible ATP-competitive ERK1/2 kinase inhibitor. By occupying the ATP-binding pocket of ERK1 (MAPK3) and ERK2 (MAPK1), it prevents downstream substrate phosphorylation, effectively terminating signal transmission along the hyperactive Ras Raf MEK ERK MAPK pathway. In KRAS-mutant neoplastic models, this catalytic blockade suppresses oncogenic transcriptional programs, arrests cell cycle progression, and induces apoptosis, offering target engagement within tumor tissues.
Intratumoral Target Engagement and Downstream Signature Suppression
Pharmacodynamic biomarker evaluation confirmed the catalytic inhibition of ERK1/2 by the Ulixertinib inhibitor within patient biopsy tissue. Differential gene expression analysis via RNA-sequencing revealed robust transcriptional suppression of downstream MAPK target genes. Downstream phosphorylation ceased within hours of administration. MAPK pathway transcriptional activity scores dropped significantly post-treatment. This target engagement validated the biochemical potency of the compound in human pancreatic tumor microenvironments. However, pathway inhibition alone proved insufficient to yield clinical superiority over standard regimens. Compensatory signaling network adjustments likely attenuated sustained apoptotic responses.
Toxicity Profile Limits Exposure in Triplet Chemotherapy Regimens
Combining ERK inhibition with doublet chemotherapy produced marked dose-limiting systemic toxicities. Over 80% of enrolled subjects experienced Grade 3 or higher treatment-related adverse events. Gastrointestinal distress and hematologic suppression occurred with elevated frequency. Treatment interruptions were necessary across most cohorts. Patient withdrawal rates escalated rapidly during initial treatment cycles. The observed objective response rate of 20% matched standard gemcitabine plus nab-paclitaxel controls. Median overall survival reached 12.23 months. Without optimized exposure windows, cytotoxic synergy remains difficult to maintain.
Optimizing Combination Schedules and Dosing Strategies
Future development of the Ulixertinib inhibitor requires modified dosing schedules to mitigate toxicities. Intermittent dosing schedules may relieve normal tissue strain while retaining therapeutic efficacy. Target inhibition profiles suggest that continuous complete target coverage is not mandatory for antitumor activity. Combining ERK inhibitors with novel targeted agents rather than full-dose cytotoxic backbones offers another clinical path. Careful selection of synergy partners will remain critical for clinical feasibility.